
Last updated on Sep 1, 2026

Banner Health Authorization to Use or Disclose Protected Health Information 2013-2026 free print...
pdfFiller is not affiliated with any government organization
Fill out
Complete the form online in a simple drag-and-drop editor.
eSign
Add your legally binding signature or send the form for signing.
Share
Share the form via a link, letting anyone fill it out from any device.

Export
Download, print, email, or move the form to your cloud storage.
Why pdfFiller is the best tool for your documents and forms


End-to-end document management
From editing and signing to collaboration and tracking, pdfFiller has everything you need to get your documents done quickly and efficiently.
Accessible from anywhere
pdfFiller is fully cloud-based. This means you can edit, sign, and share documents from anywhere using your computer, smartphone, or tablet.
Secure and compliant
pdfFiller lets you securely manage documents following global laws like ESIGN, CCPA, and GDPR. It's also HIPAA and SOC 2 compliant.
What is Banner Health Authorization to Use or Disclose Protected Health Information
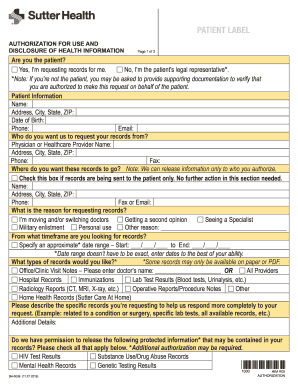
The Authorization to Use or Disclose Protected Health Information is a healthcare form used by patients or their legal representatives to authorize the release of a patient's medical records.
pdfFiller scores top ratings on review platforms




Who needs Banner Health Authorization to Use or Disclose Protected Health Information?
Explore how professionals across industries use pdfFiller.

Banner Health Authorization to Use or Disclose Protected Health Information is needed by:
-
Patients seeking to release their medical records.
-
Legal representatives managing a patient's health information.
-
Healthcare providers requiring authorization for patient records.
-
Administrators handling medical information requests.
-
Insurance companies needing access to patient health records.
Comprehensive Guide to Banner Health Authorization to Use or Disclose Protected Health Information
What is the Authorization to Use or Disclose Protected Health Information?
The Authorization to Use or Disclose Protected Health Information is a critical document within the healthcare landscape. This patient consent form facilitates effective management of patient care by allowing healthcare providers to obtain necessary information for treatment purposes. Key components of this form include the identification of patient information and explicit consent for the release of records, ensuring compliance with privacy standards. By utilizing this authorization, patients can protect their rights and maintain the confidentiality of their protected health information in the U.S.
Purpose and Benefits of the Authorization to Use or Disclose Protected Health Information
This authorization is essential for both patients and healthcare providers, particularly in scenarios involving the sharing of medical records. The use of this medical records release form empowers patients to control their health information while facilitating continuity of care between providers. Notably, it safeguards the confidentiality and security of patient information throughout the process, fostering trust in healthcare interactions.
Key Features of the Authorization to Use or Disclose Protected Health Information
Several critical features distinguish this form. The layout includes various blank fields and checkboxes catering to specific records, alongside signature lines for both patients and their legal representatives. It’s crucial to understand that this form boasts legal validity in compliance with regulatory standards, and it includes a release of liability for Banner Health, reinforcing patient protection.
Who Needs the Authorization to Use or Disclose Protected Health Information?
This form is relevant for patients and their legal representatives, who have defined roles and responsibilities regarding the release of health information. The authorization is particularly necessary in situations such as when caregivers seek permission to access a patient's records. Healthcare providers and facilities also require this form when requesting patient information for treatment or administrative purposes.
When and How to Fill Out the Authorization to Use or Disclose Protected Health Information
To properly complete the authorization, follow these steps:
-
Gather necessary patient information including the name and date of birth.
-
Specify the records to be released along with the purpose of disclosure.
-
Carefully fill out each field, ensuring accuracy to avoid processing delays.
Each section of the form must be approached with attention to detail, confirming that all information provided is correct and up-to-date.
Common Errors and How to Avoid Them When Filing the Authorization
While completing the authorization, users often encounter common pitfalls that can hinder the submission process. These may include:
-
Missing signatures, which can render the form invalid.
-
Incorrect details, such as the patient's information or specific record requests.
To prevent these mistakes, it’s advisable to thoroughly review and validate the completed form. Regular updates are also important to prevent the use of outdated forms.
Record Retention and Privacy Considerations for the Authorization
Record retention requirements are a crucial aspect of the authorization process, particularly under HIPAA regulations. Maintaining confidentiality and strong data protection measures throughout the handling of this form are essential to safeguarding patient information. Users should implement secure document management practices, such as those offered by pdfFiller, ensuring that sensitive documents remain protected.
How to Submit the Authorization to Use or Disclose Protected Health Information
Submission instructions for the authorization form can vary. Users have several options available:
-
Electronic submission through secure platforms.
-
Mailing the completed form to designated healthcare facilities.
Typical turnaround times for processing submissions can vary, and users should be aware of what to expect after their forms are submitted.
Enhancing Efficiency with pdfFiller for Authorization Forms
Utilizing pdfFiller can greatly enhance the efficiency of filling out authorization forms. Key capabilities of pdfFiller include:
-
Editing and eSigning forms securely in the cloud.
-
Facilitating easy sharing of completed documents.
The step-by-step process for using pdfFiller for the Authorization to Use or Disclose Protected Health Information simplifies document management. Importantly, pdfFiller employs robust security features to ensure sensitive information is handled safely.
Final Steps and What to Do After Submitting the Authorization
After submitting the authorization, tracking the application status is crucial. Users should verify submission confirmation and understand how to amend or update their authorizations if necessary. Leveraging pdfFiller will simplify the management of future forms and documents, resulting in a more efficient organizational process.
How to fill out the Banner Health Authorization to Use or Disclose Protected Health Information
-
1.To begin, visit pdfFiller and log in to your account. If you don’t have an account, you can easily create one.
-
2.Once logged in, locate the search bar, type 'Authorization to Use or Disclose Protected Health Information,' and select the form from the results.
-
3.The form will open in the pdfFiller editor. Familiarize yourself with the layout, including sections for patient information and checkboxes for record types.
-
4.Before filling out the form, gather necessary information such as the patient's full name, date of birth, and specific records to be disclosed.
-
5.Complete all required fields, ensuring accuracy. Click on the appropriate checkboxes to select the types of records you wish to authorize for release.
-
6.In addition, fill in the purpose of disclosure in the designated field, providing clear reasoning for the request.
-
7.If necessary, have a legal representative review the form for completeness. They will also need to sign in their respective section.
-
8.After filling out the form, carefully review all information for accuracy. Make sure all signatures and dates are properly included.
-
9.To save your work, click on the 'Save' button. You may download the form as a PDF or send it directly via email using the options available in pdfFiller.
-
10.Finally, submit the form according to your healthcare provider's instructions, ensuring that copies of the signed document are retained for your records.
Who can fill out the Authorization to Use or Disclose Protected Health Information form?
The form can be filled out by the patient or their legal representative. It's important that the person signing has the authority to make healthcare decisions on behalf of the patient.
Are there any deadlines for submitting this authorization form?
While the specific deadlines can vary, it’s advisable to submit the authorization as soon as possible, particularly if the records are needed for an upcoming appointment or procedure.
How do I submit the completed form?
You can submit the completed form to your healthcare provider directly, either in person or via mail, based on their submission requirements. Some may also accept electronic submissions.
What information do I need to provide on the form?
You will need to provide the patient's identifying details, the specific medical records to be released, and the purpose of the disclosure. Ensure all required fields are completed accurately.
What are common mistakes to avoid when completing this form?
Common mistakes include leaving required fields blank, not providing the patient's full name or details accurately, and failing to obtain the necessary signatures. Double-check all entries before submission.
How long does it take to process the authorization once submitted?
Processing times can vary based on the healthcare provider but typically range from a few days to a couple of weeks. It's best to inquire directly with the provider for their specific timeline.
Do I need to notarize the form?
No, notarization is not required for this authorization form. However, it must be signed by the patient or their legal representative to be valid.
Banner Health Authorization to Use or Disclose Protected Health Information Form Versions
Related Content
Related Forms



If you believe that this page should be taken down, please follow our DMCA take down process
here
.
This form may include fields for payment information. Data entered in these fields is not covered by PCI DSS compliance.